



Hysterectomy for Adenomyosis
A hysterectomy removes the uterus, the source of the heavy bleeding and cramping adenomyosis causes. It's the only treatment that reliably removes adenomyosis itself, and it's considered when symptoms stay severe despite other options.
- How
- Robotic, minimally invasive
- Home
- Same day or short stay
- Recovery
- 2–6 weeks to build back up
Medically reviewed by Dr. Steven Vasilev, MD
Board-Certified Gynecologic Oncologist & Integrative Medicine Diplomate, Advanced Robotic Endometriosis Excision Surgeon, Director of Lotus Endometriosis Institute · Updated Nov 2026
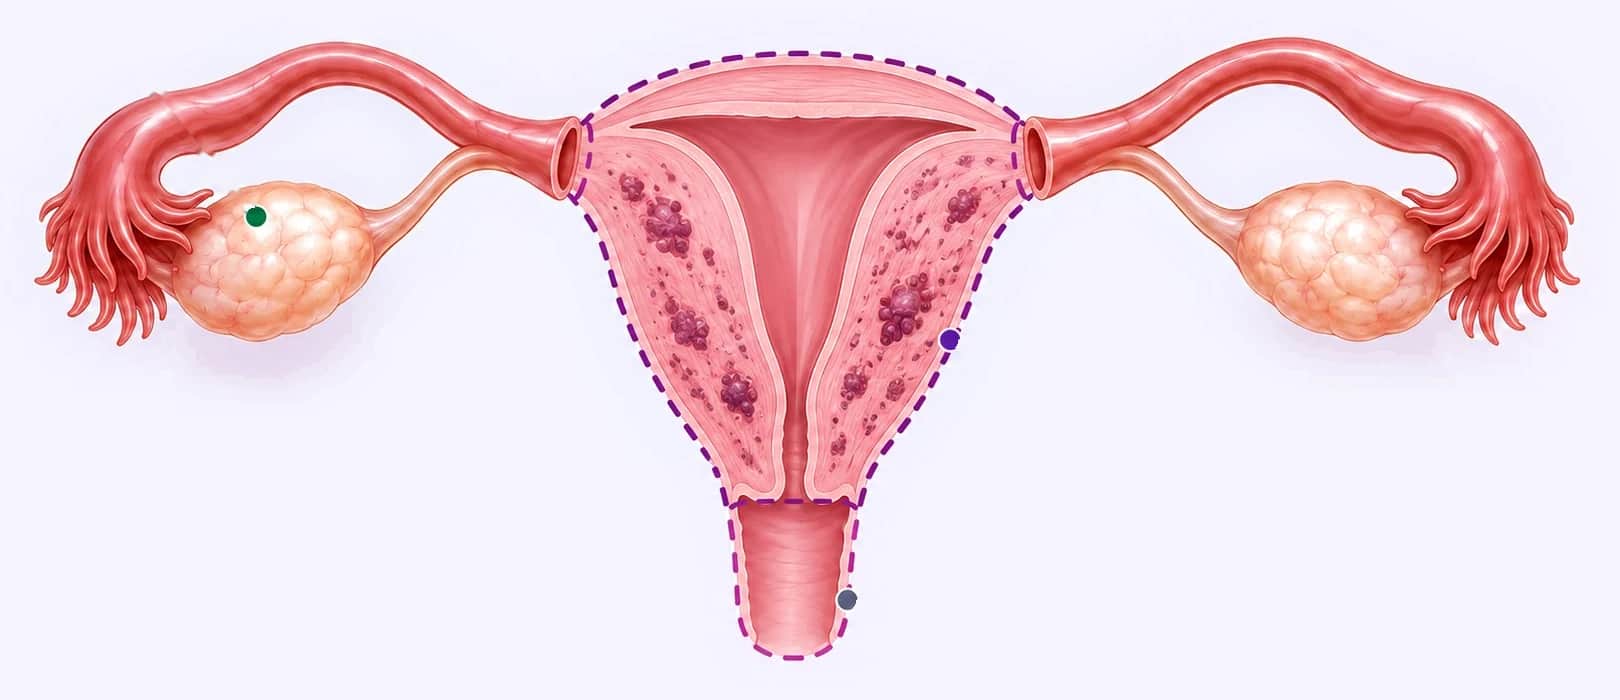
- Uterus: removedAdenomyosis is in its wall.
- Cervix: removed or keptDecided with you.
- Ovaries: often keptAvoids sudden menopause.
RemovedAdenomyosis in the muscle wall
Why the ovaries matter
Removing the ovaries lowers estrogen but causes immediate menopause and can affect long-term health. Keeping them often avoids that. The choice is made with you, based on your age, symptoms, risk factors and goals.
Who it’s for
Is it right for me?
When heavy bleeding, cramping or pain stay severe despite other treatment, and you're sure you don't want a future pregnancy.
Heavy bleeding can mean soaking through, passing clots, or low iron. Cramping and pressure can mean daily pain or heaviness despite treatment. When it reaches your sleep, work, intimacy or mood, it's affecting your whole life.
Adenomyosis can show on MRI or a specialized ultrasound. Hysterectomy is worth considering once other treatments, such as hormones or an IUD, haven't been enough, and only if you're sure you don't want a future pregnancy.
You won't be able to carry a pregnancy afterwards.
Often improves
- Heavy bleeding and clots
- Cramping and pelvic pressure
- Pain that follows your cycle
- Tiredness from anemia, once bleeding stops
Won’t fix on its own
- Endometriosis elsewhere in the pelvis (it needs excision, often in the same operation)
- Pelvic floor tension or nerve sensitization
If endometriosis is there too, it's removed in the same operation, and pelvic floor therapy or pain care can follow.
Your options
How does it compare?
It's the only option that removes adenomyosis completely. Uterus-sparing options keep pregnancy possible but may not end the symptoms.
The choice turns on pregnancy. If symptoms are severe and you're done having children, hysterectomy removes adenomyosis completely, and pregnancy isn't possible afterwards. If you want a pregnancy and the adenomyosis is focal, uterus-sparing surgery removes part of it and keeps the uterus.
Hormones, an IUD or other treatment remove nothing, but can ease symptoms. They suit milder symptoms, or a time when you're not ready for surgery. Endometriosis found alongside adenomyosis can be excised in the same operation as a hysterectomy.
| Compared | Hysterectomy | Uterus-sparing surgery | Hormones, IUD or other treatment |
|---|---|---|---|
| Removes adenomyosis | Completely | Partly, for focal disease | No; eases symptoms |
| Pregnancy afterwards | Not possible | Possible | Possible |
| Often right for | Severe symptoms, done having children | Focal adenomyosis, wanting a pregnancy | Milder symptoms, or not ready for surgery |
Hysterectomy
- Removes adenomyosis
- Completely
- Pregnancy afterwards
- Not possible
- Often right for
- Severe symptoms, done having children
Uterus-sparing surgery
- Removes adenomyosis
- Partly, for focal disease
- Pregnancy afterwards
- Possible
- Often right for
- Focal adenomyosis, wanting a pregnancy
Hormones, IUD or other treatment
- Removes adenomyosis
- No; eases symptoms
- Pregnancy afterwards
- Possible
- Often right for
- Milder symptoms, or not ready for surgery
From first visit to recovery
What happens, step by step?
A video consultation, tests such as MRI and bloodwork, a plan for your ovaries and cervix, then one operation and a few weeks of recovery.
It starts with a video consultation about your symptoms, what you've tried, and whether you're certain you don't want a future pregnancy. Testing often includes MRI or a specialized ultrasound, and bloodwork including iron levels if bleeding has been heavy. Together we decide whether your cervix and ovaries are kept, and whether endometriosis is removed in the same operation. Insurance and a fixed price are settled before anything is booked.
The operation is robotic, through small incisions, and you often go home the same day or after a short stay. Most people build activity back up over 2–6 weeks, though internal healing takes longer. A short in-person check follows, then a video visit at three months.
Before surgery
Planning consultation
By video: your symptoms, what you've tried, and whether you're certain you don't want a future pregnancy.
We also look for endometriosis and for conditions that can mimic adenomyosis, because they change the plan.
Testing
Often MRI or a specialized ultrasound, bloodwork including iron levels if bleeding has been heavy, and tests such as a SIBO breath test when symptoms overlap.
Your plan
Together we decide whether the cervix and ovaries are kept, and whether endometriosis will be removed in the same operation. Insurance and a fixed price are settled before anything is booked.
Surgery day
The operation
Robotic, through small incisions. The uterus is removed, and any endometriosis found is excised in the same operation.
Often in the same operation: endometriosis excision
Going home
Day 0–1
Often the same day, or after a short hospital stay.
Recovery
Early recovery
Weeks 1–2
Tiredness, soreness and a tugging feeling when you move are common. Pace yourself; rest is part of healing.
Building back up
Weeks 2–6
Most people increase activity gradually over 2–6 weeks. Internal healing takes longer, even when the incisions look fine.
If pelvic muscle tension, or pain with sitting, bowel movements or sex continues, pelvic floor therapy can be an important part of recovery.
Follow-up
Checks and follow-up
Follow-up
A short in-person check of internal healing, then a video visit at 3 months.
Call us promptly for fever, worsening pain, heavy bleeding, shortness of breath, or worrying bladder or bowel symptoms.
Your surgeon
Who should do it?
A surgeon who also excises endometriosis. The two often occur together, and both can be treated in the same operation.
Adenomyosis often comes with endometriosis. A surgeon who also excises endometriosis can treat both in one operation, so the hysterectomy isn't the end of the road but one part of a complete plan.
“A hysterectomy may not be the complete solution. If endometriosis is also found, it should be excised in the same operation.”
Patients often ask
When is hysterectomy recommended for adenomyosis?
Hysterectomy is typically considered for adenomyosis when severe symptoms come from the uterus and you’re not planning future pregnancy. It is usually weighed most strongly when conservative treatments haven’t provided acceptable relief, aren’t tolerated, or don’t fit your goals.
Is uterine artery embolization (UAE) right for adenomyosis?
UAE can be a good fit for adenomyosis when your goal is symptom relief while preserving the uterus, especially for heavy bleeding. Whether it’s right depends on your symptoms, fertility goals and whether endometriosis is also contributing.
Can adenomyosis come back after hysterectomy?
In the usual sense, adenomyosis does not come back after a total hysterectomy, which removes the uterus and cervix. Some people still have pain or other symptoms afterward, usually from overlapping conditions, especially endometriosis, which hysterectomy alone does not cure, or from a nervous system sensitized to pain.
When is pain after hysterectomy concerning?
Pain after hysterectomy is concerning when it isn’t improving or suddenly worsens after improvement. Severe or progressive pain, or pain with fever, heavy bleeding, chest pain, shortness of breath, or urinary or bowel changes, is worth prompt evaluation.
You’re on step 1 of 3
Next: Who should operate?What to look for in any surgeon, and Dr. Vasilev’s results.