




Focal Adenomyosis Imaging, Diagnosis, and Next Steps
Understand your imaging report, symptoms, and options for treatment and fertility planning.

Focal adenomyosis means a concentrated area, not necessarily mild disease
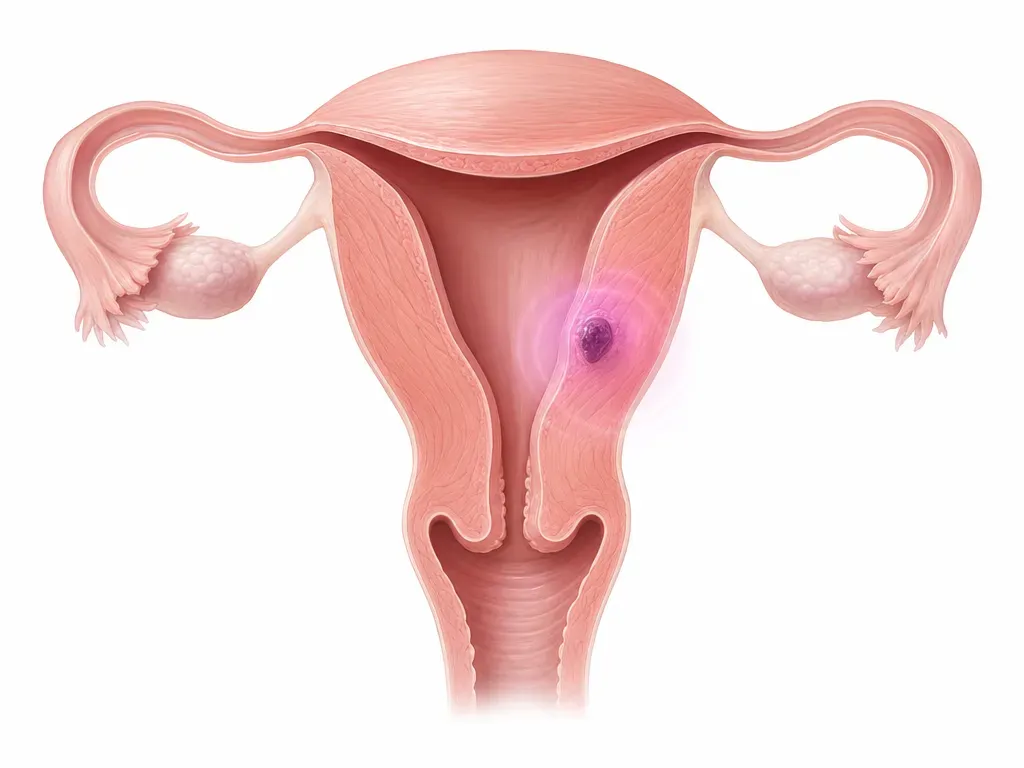
Focal adenomyosis means adenomyosis-related changes are concentrated in one area of the uterine muscle rather than spread throughout it. A mass-like area may be called an adenomyoma and can closely resemble a fibroid on imaging. A focal finding can cause substantial pain or bleeding, and it may change diagnostic or surgical discussions, especially if you are concerned about fertility.
Focal and diffuse adenomyosis frequently coexist. Even when imaging identifies a focal lesion, more widespread disease is present in many patients. Focal does not automatically mean mild, isolated, or easy to treat.
Your report may describe a localized area of heterogeneous myometrial texture, meaning the uterine muscle looks uneven in that region. MRI may also show regional changes in the junctional zone, the inner muscle layer bordering the uterine lining.
A small focal finding can still cause severe symptoms
Symptom severity does not reliably track with how large a lesion looks on imaging. A relatively small focal lesion can be associated with:
- Heavy or prolonged menstrual bleeding.
- Severe cramping or cyclical pelvic pain.
- Pain with intercourse.
- Fertility challenges.
Imaging should guide which treatments are possible, but it should never be used to dismiss symptoms. When pain or bleeding is greater than imaging seems to explain, your doctor should also consider overlapping contributors such as fibroids, endometriosis, pelvic floor dysfunction, bladder or bowel pain, or anemia. Care should be symptom-led and adapt as your goals change.
How ultrasound and MRI clarify the diagnosis
Transvaginal ultrasound
Transvaginal ultrasound is usually the first step and can be very informative in experienced hands. Radiologists increasingly use standardized frameworks to describe features suggestive of adenomyosis, including small cysts within the uterine muscle, lines or buds extending from beneath the lining, and focal junctional-zone irregularity.
A 2024 narrative review of diagnosis, treatment, and fertility in women with adenomyosis distinguished direct ultrasound signs, such as myometrial cysts, from indirect signs, such as wall asymmetry and junctional-zone changes. When only indirect or borderline features are present, diagnostic certainty may be lower. Clarification or follow-up imaging is reasonable, particularly if treatment decisions hinge on the diagnosis.
MRI when the lesion or treatment plan needs clarification
MRI is often most helpful in focal disease when specific questions need answers:
- Is this truly a fibroid, or could it be an adenomyoma?
- How deep is the lesion within the uterine wall?
- Does it distort or approach the uterine cavity?
- Are there other findings, such as endometriosis, that change management?
MRI tends to be highly specific for adenomyosis, making it particularly useful when surgery, fertility treatment, or another invasive procedure is being considered. The purpose is to clarify findings that could change your options or the risks of a proposed treatment.
Reading your report for details that affect decisions
Adenomyosis classification and report language are not standardized, so reports can feel inconsistent or vague. A 2023 review of imaging and tissue-based classification systems for adenomyosis found no consensus on a single system. Focus on the details that could change treatment rather than the label alone.
Location tells you where the finding sits. Focal posterior adenomyosis is in the back wall of the uterus, while focal anterior adenomyosis is in the front wall. A report may also place the lesion at the fundus, the top of the uterus, or near the cervix.
Size, depth, and relationship to the uterine cavity help determine which treatments are feasible and what risks matter. Ask how much of the muscle wall is involved and whether the lesion approaches or distorts the cavity. Junctional-zone findings on MRI also help describe the pattern of disease.
The report should also address coexisting fibroids or signs of endometriosis. The phrase “focal lesion in uterus” alone does not settle whether the finding is an adenomyoma or a fibroid. If that distinction could change treatment, an imaging review or second opinion can be useful.
Diagnosed with Focal Adenomyosis? Explore Your Next Steps
Our specialists are here to help you understand your condition and explore your treatment options.
Schedule a ConsultationMedical treatment starts with your priorities
The right approach depends on your priorities: symptom control, fertility, avoiding hormones, avoiding surgery, or definitive treatment. Medical therapy is often the first step, but the plan should reflect what matters most to you.
A 52 mg levonorgestrel-releasing IUD is commonly used for bleeding and pain control. It works well for many patients when the uterine cavity is not significantly distorted.
Oral hormonal options, including combined oral contraceptives or progestins, can also reduce pain and bleeding. These may be used continuously to suppress cycles.
GnRH agonists or antagonists are sometimes used short-term for severe symptoms or in fertility-related settings. They are generally not long-term standalone solutions because of side effects.
A fair trial of medical therapy usually requires several cycles, and sometimes up to six months, to judge effectiveness. Discuss with your doctor how you will assess improvement and when to revisit the plan if symptoms remain severe.
Uterus-sparing procedures and surgery
When symptoms remain severe despite appropriate medical therapy, additional options may be discussed. Fertility goals and the possibility of coexisting diffuse adenomyosis must remain central to that decision.
Adenomyomectomy
In carefully selected cases, surgical removal of a focal adenomyoma, called adenomyomectomy, may be considered, particularly for people pursuing pregnancy. This is technically demanding surgery, and outcomes depend heavily on surgeon experience. Future pregnancy risks, including uterine rupture, must be discussed in detail.
Up to 60% of adenomyomas are associated with diffuse adenomyosis. A prevailing view is that diffuse adenomyosis is the background problem, with an aggregation in one or two areas forming adenomyotic masses. Removing the visible mass therefore may leave substantial disease behind.
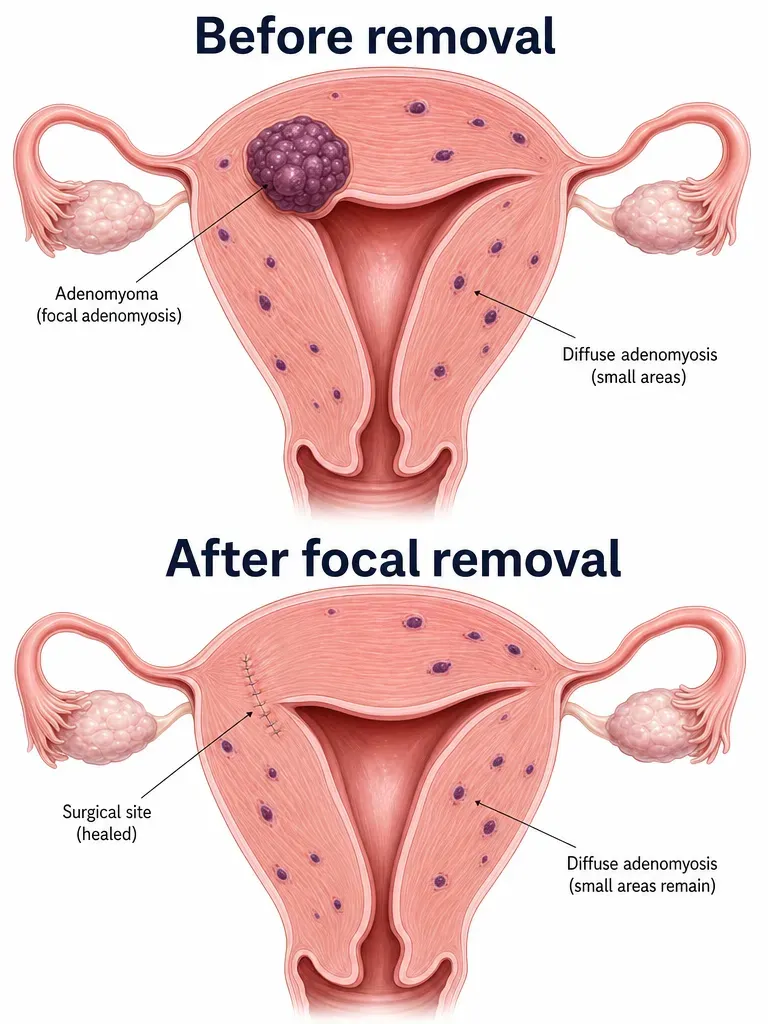
Excision is problematic for several reasons, including bleeding and effects on future pregnancies. There is a very real possibility of leaving diffuse adenomyosis behind and gaining no real overall benefit. The decision must be highly individualized, with an in-depth discussion of risks versus benefits and the surgeon’s experience with this procedure.
Other procedures
Energy-based treatments or uterine artery embolization may be discussed in some settings. Outcomes vary widely, and many patients still require hormonal suppression afterward because of coexisting diffuse disease. If pregnancy is a goal, that needs to be part of the discussion before choosing a procedure.
Hysterectomy
When childbearing is complete and symptoms are life-altering, hysterectomy remains the definitive treatment for adenomyosis. The decision should still account for coexisting endometriosis or other sources of pain, which require their own assessment and treatment plan.
When to seek more clarity and what to ask
Reasons to revisit the diagnosis or plan
Further imaging or specialist consultation may help when it is unclear whether a lesion is a fibroid or an adenomyoma, or when fertility planning requires precise mapping of the uterus. Persistent severe symptoms after appropriate medical trials and suspected coexisting endometriosis are also reasons to revisit the diagnosis or treatment plan.
If you’d like a second opinion on your imaging or a recommended treatment, our team at Lotus Endometriosis Institute can review it. A specialist’s assessment can help clarify which findings matter for your symptoms, fertility goals, and treatment choices.
Questions for your doctor
- How confident are we that this lesion is focal adenomyosis rather than a fibroid?
- Does its location or depth affect bleeding, pain, or fertility?
- Would MRI change my treatment options?
- What is the stepwise plan if first-line treatment doesn’t help?
- If surgery is considered, what are the implications for pregnancy and delivery?
References
Moawad G, Fruscalzo A, Youssef Y, et al. Adenomyosis: An Updated Review on Diagnosis and Classification. Journal of Clinical Medicine. 2023. () DOI: 10.3390/jcm12144828
Selntigia A, Molinaro P, Tartaglia S, Pellicer A, Galliano D, Cozzolino M. Adenomyosis: An Update Concerning Diagnosis, Treatment, and Fertility. Journal of Clinical Medicine. 2024. () DOI: 10.3390/jcm13175224
Ottolina J, Villanacci R, D’Alessandro S, et al. Endometriosis and Adenomyosis: Modern Concepts of Their Clinical Outcomes, Treatment, and Management. Journal of Clinical Medicine. 2024. () DOI: 10.3390/jcm13143996
Quick Answers
Which adenomyosis symptoms most affect daily life?
Heavy or prolonged periods and severe period pain usually cause the biggest disruption to daily life with adenomyosis. Bleeding can affect work, school, travel, and sleep, while fatigue, pelvic pressure, and pain with sex for some people can add to the burden.
Why do I look pregnant from bloating with constant pelvic pressure?
Bloating that makes you look pregnant with constant pelvic pressure can come from pelvic inflammation, swelling, or a sense of bulk. Endometriosis, adenomyosis, fibroids, ovarian cysts, and bowel sensitivity can contribute, and symptoms alone don’t reliably identify the cause.
Why does ovarian cyst pain keep coming back?
Ovarian cyst pain can return because new cysts form with ovulation, a cyst persists or comes back, or nearby endometriosis or scar-like bands cause pain. An endometrioma, a cyst caused by endometriosis, may be associated with deeper pelvic disease.
Why do I get low back and leg pain during my period?
Low back and leg pain during your period can happen when pelvic inflammation irritates pain pathways that send pain into your back and legs. In some patients, endometriosis can play a role, but pain can also come from the spine, hips, or muscles.