




Supplements for Adenomyosis and Endometriosis, what helps?
A guide to herbal medicines, symptom and fertility evidence, safety, and questions for your doctor

Supplements for adenomyosis and endometriosis in brief
No supplements for adenomyosis or endometriosis have strong human evidence showing that they reliably shrink disease or cure either condition. Some supplements and herbal medicines may be worth discussing as symptom-focused additions to standard care, particularly for pain or inflammation. The stronger pooled human findings for fertility supplements chiefly concern people with diminished ovarian reserve, not endometriosis or adenomyosis themselves.
Pain, heavy bleeding, fatigue, fertility concerns, and the limits or side effects of standard treatments are understandable reasons to explore supplements, probiotics, and herbal medicines. But symptom relief, a change on imaging, and improved fertility are different outcomes. Choosing an option starts with identifying which outcome matters to you and how you and your doctor will judge its benefit and safety.
Why supplements and herbal medicines draw interest
Endometriosis lesions have an active inflammatory environment, with signals that promote inflammation, new blood-vessel growth, oxidative stress, and abnormal tissue survival. Plant compounds are being examined because some can interfere with these processes.
A 2025 mechanistic review covering laboratory, animal, and human findings relevant to endometriosis described several cellular signaling pathways that plant compounds may affect. These include NF-κB, which regulates inflammation; COX-2/prostaglandins, involved in inflammation and pain; PI3K/Akt, involved in cell survival; and Nrf2/ARE, involved in defenses against oxidative stress.
The proposed advantage is that some compounds may target local inflammatory and oxidative signaling rather than suppressing estrogen throughout the body, as many hormonal medications do. That provides a biological reason to test them as additions to standard care. It does not prove that taking a supplement treats endometriosis or adenomyosis.
Evidence for changes in lesions and adenomyosis imaging
Lesion findings in an animal model
In a 2025 experimental study of mice with surgically induced endometriosis, an oral extract of Paeonia lactiflora root, or white peony, was associated with smaller lesion diameter. Levels of TNF-α, an inflammatory signal, and VEGF, a driver of new blood vessels, also decreased in abdominal fluid. This supports the idea that reducing inflammation and blood-vessel signaling may make lesions less able to sustain themselves.
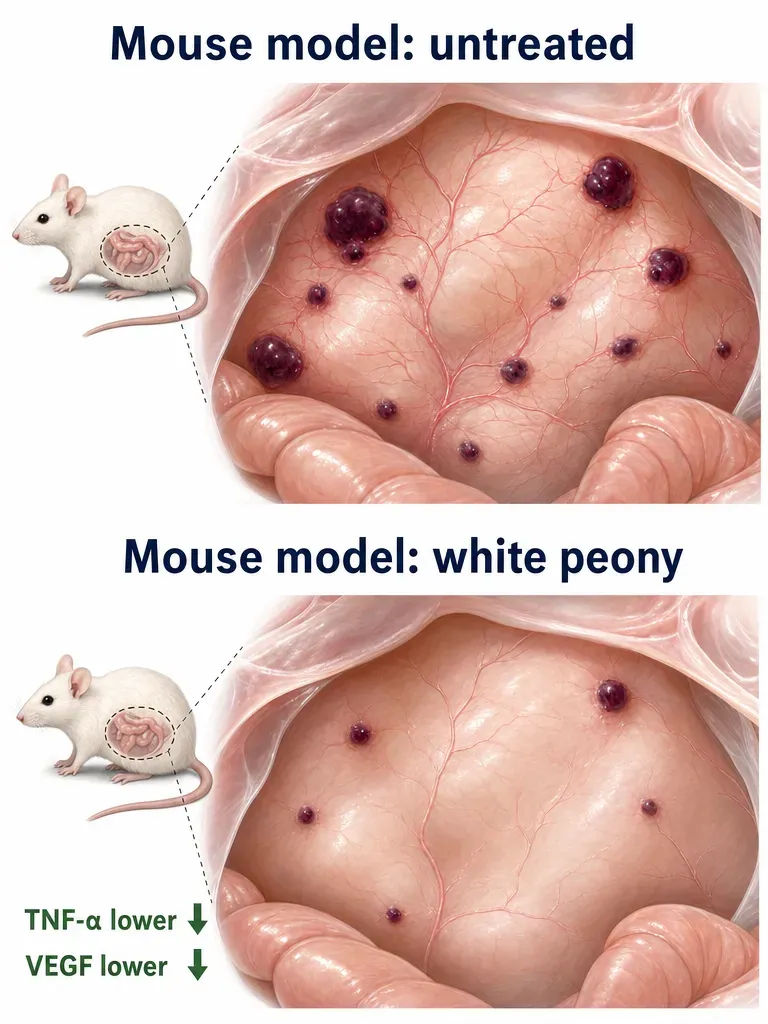
However, the quality of animal models of endometriosis and adenomyosis remains debated. Surgically induced lesions in mice are not equivalent to years of disease in humans, and effective human dosing and safety have not been established. Higher doses also showed toxicity in animals, making these results hypothesis-generating, not a recommendation for human use.
Adenomyosis changes in a monitored case
A 2025 case report followed a 40-year-old woman with ultrasound findings supporting adenomyosis who took a modified traditional Korean herbal formula, Bojungikgi-tang. Over roughly 12 months, pain and bleeding scores improved, hemoglobin was reported to normalize, and ultrasound findings suggested improvement in adenomyosis features.
The case provides an example of monitoring symptoms alongside blood tests and imaging. It cannot show that the formula caused the changes: hormonal contraception was reduced but continued, and adenomyosis symptoms can fluctuate over time. Evidence that supplements or herbs produce actual lesion or adenomyosis regression remains limited and low-strength, largely consisting of animal findings and individual cases rather than robust human trials.
Evidence for pain and heavy bleeding
Pain and inflammation
Some plant compounds have anti-inflammatory or antioxidant actions that overlap with pathways involved in endometriosis pain. The 2025 mechanistic review of laboratory, animal, and human findings relevant to endometriosis highlighted curcumin from turmeric, ginger constituents such as shogaol, licorice-derived isoliquiritigenin, and milk-thistle compounds such as silymarin and silibinin. Their actions include reducing NF-κB signaling or COX-2/prostaglandin activity.
These are mechanistically interesting compounds, not proven endometriosis treatments. The more concrete human trials discussed in that review largely involved primary dysmenorrhea, meaning menstrual pain without an identified underlying condition, rather than confirmed endometriosis. Painful periods overlap with endometriosis symptoms, but benefits in one group cannot automatically be applied to the other.
A symptom-focused supplement may therefore be reasonable to discuss with your doctor, especially for pain or inflammation. Expectations should remain realistic because direct human evidence in confirmed endometriosis and adenomyosis is still very thin.
Heavy bleeding and anemia
Heavy bleeding can be as disruptive as pain, particularly when it causes anemia and fatigue. In the 2025 case report of the woman taking modified Bojungikgi-tang for suspected adenomyosis, the menstrual bleeding score fell from over 400 to approximately 55, and clots and flooding stopped. Menstrual pain decreased from 7–8 to 1–2 on a 10-point scale, alongside the reported recovery from anemia.
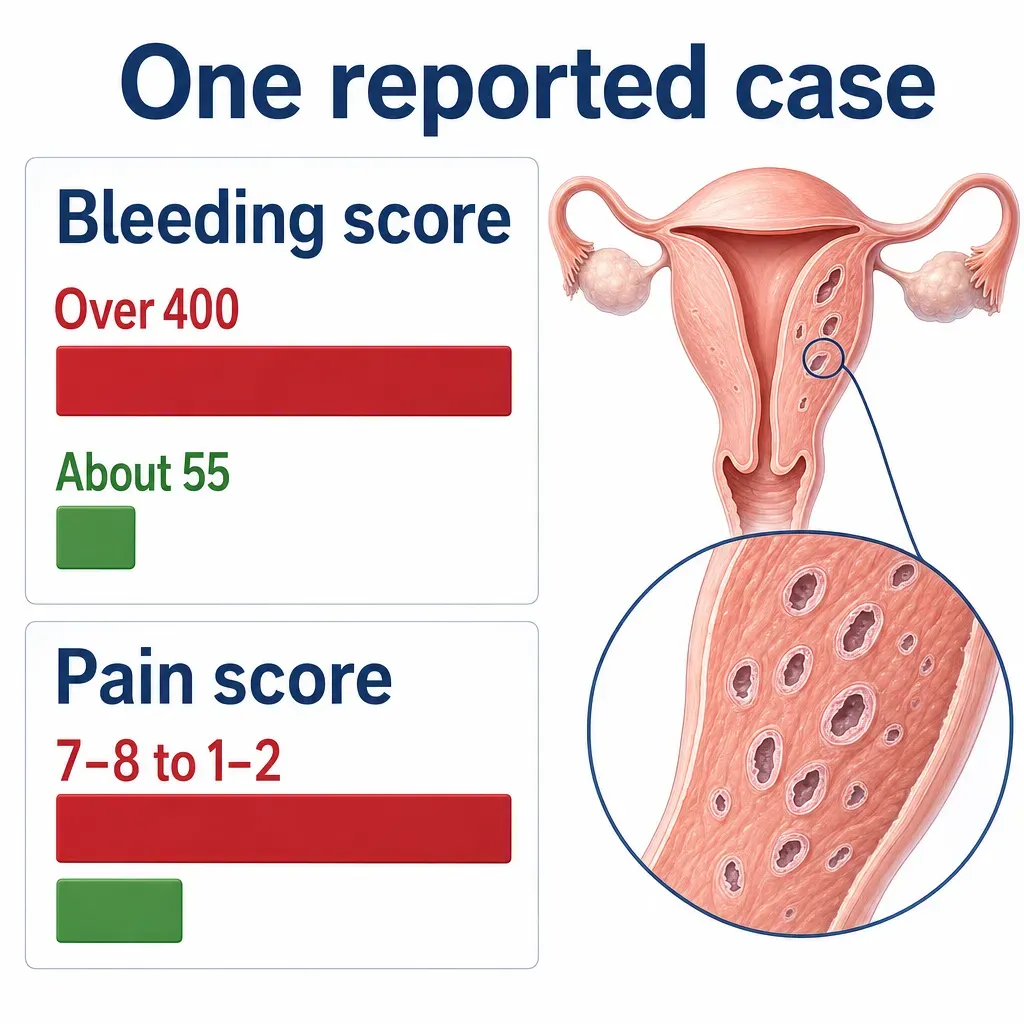
Those are meaningful changes in daily life, but one person’s improvement does not establish that an herbal formula will reduce bleeding for others. The continued hormonal treatment also prevents attributing the benefit to the formula alone. If bleeding is the treatment goal, tracking blood loss and anemia is more informative than relying only on a general sense of feeling better.
Fertility and implantation evidence
Implantation signals in mice
In the 2025 experimental study of mice with induced endometriosis, white peony extract also affected implantation-related measures. Endometriosis reduced uterine expression of leukemia inhibitory factor, or LIF, a gene associated with implantation, and lowered implantation rates. After treatment, LIF expression and the number of implantation sites increased.
This connects the extract to a biologically relevant implantation pathway. It does not establish a benefit in human uterine tissue, improved implantation in people, or a higher chance of live birth.
Ready to Explore Safe Supplement Options?
Our specialists are here to help you understand your condition and explore your treatment options.
Schedule Your ConsultSupplements studied in diminished ovarian reserve
A 2025 systematic review and meta-analysis combined 16 studies involving 2,773 women with diminished ovarian reserve, often undergoing IVF or related fertility treatment. It evaluated oral supplements including vitamins, coenzyme Q10, and DHEA. Supplementation was associated with lower follicle-stimulating hormone levels, slightly higher anti-Müllerian hormone levels and antral follicle counts, slightly more eggs retrieved, and higher clinical pregnancy rates.
Follicle-stimulating hormone and anti-Müllerian hormone are commonly shortened to FSH and AMH, while antral follicle count is shortened to AFC. These measures help assess ovarian reserve and response to treatment; they are not interchangeable with live birth. The pooled difference in egg retrieval was modest, averaging less than one additional egg.
Subgroup analyses suggested that CoQ10 might perform better than DHEA and that use for more than two months was associated with better changes in some measures, including FSH, AMH, and egg numbers. These findings may be relevant if you have a confirmed diagnosis of diminished ovarian reserve.
Diminished ovarian reserve is a separate diagnosis, and not everyone with endometriosis has it. These findings do not establish CoQ10, DHEA, or vitamins as fertility treatments for endometriosis or adenomyosis. Ask your fertility doctor whether an ovarian-reserve supplement applies to your diagnosis rather than choosing it solely because you have either condition.
Findings from other conditions have limits
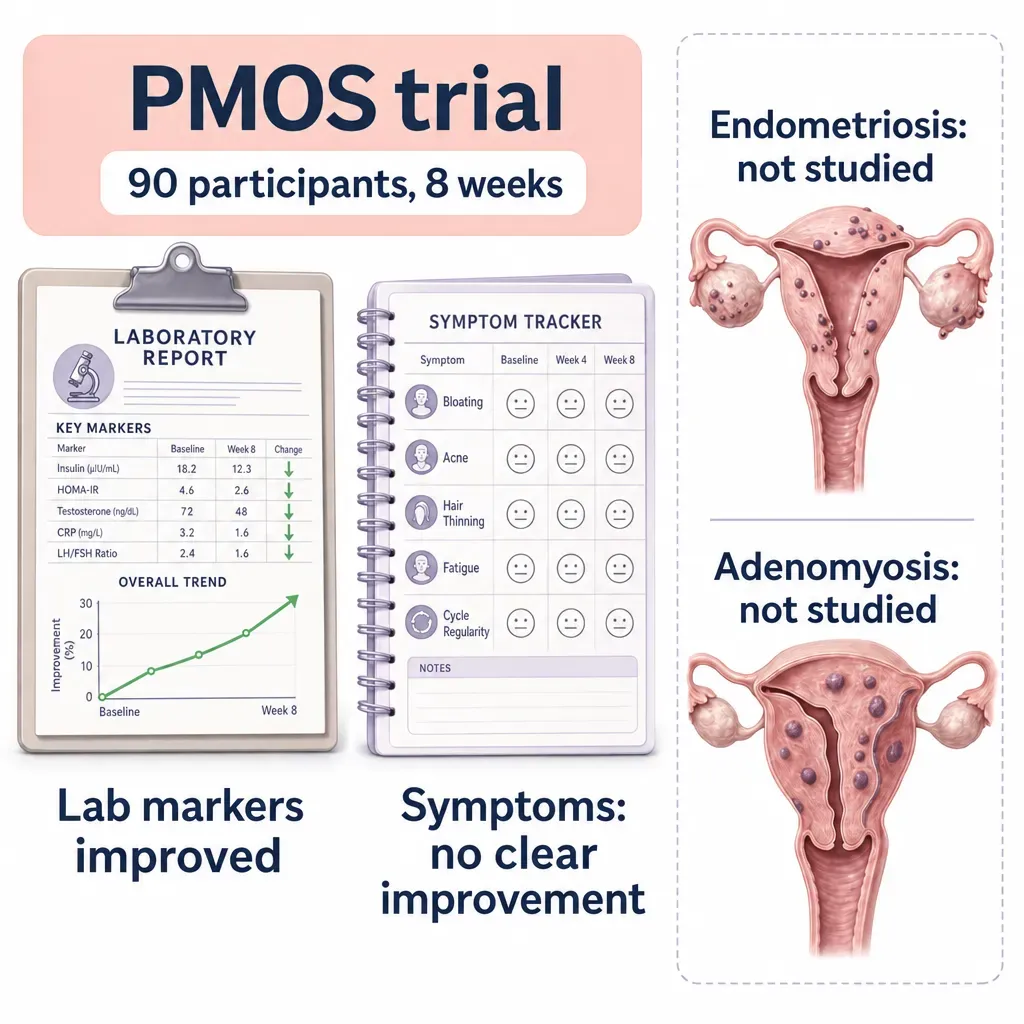
A 2025 double-blind, placebo-controlled randomized trial enrolled 90 women with PMOS, not endometriosis or adenomyosis. Participants received a combination of Lactobacillus helveticus and Bifidobacterium longum or a placebo for eight weeks alongside standard care.
The probiotic group had improvements in several blood markers: antioxidant capacity and superoxide dismutase activity increased, while malondialdehyde and C-reactive protein decreased. These changes suggest improved antioxidant defenses and reduced oxidative stress and inflammation. Sex hormone-binding globulin increased, and the free androgen index decreased, indicating changes in some hormone-related measures.
However, acne, hair loss, and excess hair growth did not clearly improve compared with placebo during that short period. A favorable laboratory result does not guarantee a noticeable symptom benefit, particularly within weeks. Because endometriosis and adenomyosis were not studied, the findings cannot be assumed to apply to either condition.
Safety and interactions matter
Natural does not mean low-risk. Supplements and herbal medicines can have real biological effects, which means they can also cause side effects and interact with medicines. Herbal formulas vary by manufacturer and preparation, and quality control can be uneven.
Higher doses of inadequately studied supplements, including herbs, botanicals, and vitamins, are not better and may cause toxicity. The higher-dose toxicity seen in the white peony animal experiment is a direct reminder of that risk. Excessive vitamin intake can also be harmful.
DHEA can cause acne, hair changes, and mood changes, and it is not appropriate for everyone. Its availability as a supplement does not make it a suitable fertility treatment without an individualized assessment.
If you are pursuing IVF or preparing for surgery, disclose everything you take to your own fertility team or surgeon. Some products may affect bleeding risk, how the body processes anesthesia, or laboratory results.
It is easy to go down rabbit holes and worsen problems by combining supplements and herbs that interact negatively. Beware of expensive miracle mixes that overpromise, underdeliver, and can hurt you. Adding more products is not a substitute for checking whether each one is useful and safe.
Choosing and monitoring an adjunct
There is no defensible single best supplement for adenomyosis or endometriosis that suits everyone. A useful choice depends on your goal, diagnosis, current treatments, and a clear plan to monitor results.
Take these three questions to your own clinician:
- What is my goal: pain control, bleeding reduction, fertility support, or better daily functioning? Different goals point to different evidence. A symptom-focused supplement and a fertility adjunct need to be judged by different outcomes.
- What evidence applies to me? Ask whether the findings concern confirmed endometriosis or adenomyosis, rather than diminished ovarian reserve, PCOS, or an animal model.
- What is the plan for monitoring and stopping? Decide in advance what success means and when to stop or reassess. Relevant measures may include a pain scale, menstrual bleeding score, hemoglobin and ferritin levels, or IVF-cycle results.
Bring a complete list of hormonal medicines, NSAIDs, anticoagulants, IVF supplements, herbs, and vitamins. This lets your clinician assess the whole regimen rather than considering a new product in isolation.

What remains uncertain
High-quality human trials in confirmed endometriosis or adenomyosis are still insufficient to identify which supplements consistently improve pain, bleeding, lesion burden, or live birth. Laboratory effects can also fail to translate because the body does not absorb enough of a compound. Curcumin is a familiar example: oral absorption can be poor unless specialized formulations are used.
Results also vary because symptom patterns, lesion type, and prior treatments differ. Coexisting irritable bowel syndrome, pelvic-floor dysfunction, diminished ovarian reserve, or PCOS can influence whether a supplement appears to help and which symptoms actually change.
If a supplement is not helping, use the planned reassessment to discuss the unmet goal with your own clinician. A focused discussion about persistent pain, bleeding, anemia, or fertility is more useful than escalating doses or adding another interacting product.
References
Abdolmaleki, Amirsayyafi, Khazaiel et al. Formulation of Paeonia lactiflora root extract can induce atrophy of endometriotic lesions and accelerate embryo implantation following in vitro fertilization in endometriosis: An experimental study. Clinical and Experimental Reproductive Medicine. 2025.. DOI: 10.5653/cerm.2024.07374
Burdan, Picheta, Piekarz et al. Mechanistic Insights into the Anti-Inflammatory and Anti-Proliferative Effects of Selected Medicinal Plants in Endometriosis. International Journal of Molecular Sciences. 2025.. DOI: 10.3390/ijms262210947
Shirani, Bagherniya, Sadeghi et al. Effects of supplementation with two probiotic strains ( Lactobacillus helveticus and Bifidobacterium longum ) on hormonal status, oxidative stress, and clinical symptoms in women with polycystic ovary syndrome: a randomized clinical trial. Nutrition Journal. 2025.. DOI: 10.1186/s12937-025-01240-3
Li, Zhao, Lin et al. The auxiliary effect of oral nutritional supplements on fertility in women with diminished ovarian reserve: a systematic review and meta-analysis. Annals of Medicine. 2025.. DOI: 10.1080/07853890.2025.2583330
Park, Jeong, Kim et al. Management of symptoms of suspected adenomyosis uteri using herbal medicine modified Bojungikgi-tang: a case report with ultrasound monitoring. Frontiers in Medicine. 2025.. DOI: 10.3389/fmed.2025.1679449
Quick Answers
When is hysterectomy recommended for adenomyosis?
Hysterectomy is typically considered for adenomyosis when severe symptoms come from the uterus and you’re not planning future pregnancy. It is usually weighed most strongly when conservative treatments haven’t provided acceptable relief, aren’t tolerated, or don’t fit your goals.
Which adenomyosis symptoms most affect daily life?
Heavy or prolonged periods and severe period pain usually cause the biggest disruption to daily life with adenomyosis. Bleeding can affect work, school, travel, and sleep, while fatigue, pelvic pressure, and pain with sex for some people can add to the burden.
Why do I look pregnant from bloating with constant pelvic pressure?
Bloating that makes you look pregnant with constant pelvic pressure can come from pelvic inflammation, swelling, or a sense of bulk. Endometriosis, adenomyosis, fibroids, ovarian cysts, and bowel sensitivity can contribute, and symptoms alone don’t reliably identify the cause.
Why does ovarian cyst pain keep coming back?
Ovarian cyst pain can return because new cysts form with ovulation, a cyst persists or comes back, or nearby endometriosis or scar-like bands cause pain. An endometrioma, a cyst caused by endometriosis, may be associated with deeper pelvic disease.